一、临床问题
患儿4岁,发热2天起病,病程中相继出现以下表现:双侧眼球结膜充血;口唇干红、杨梅舌,口咽部黏膜弥漫性充血;多形性皮疹;掌跖潮红伴硬性水肿;颈部多发淋巴结肿大(最大2.5 cm×1.1 cm,质软、无触痛、无粘连)。辅助检查:白细胞10.4×10⁹/L,C反应蛋白(CRP)49 mg/L,血清淀粉样蛋白A(SAA)>200 mg/L,红细胞沉降率(ESR)77 mm/1 h,丙氨酸转氨酶(ALT)188 U/L;腺病毒、流感病毒、肺炎支原体、鼻病毒核酸检测均阴性。现发病第3日。超声心动图检查:未见异常,冠状动脉无扩张,Z值<2。
二、"发病第5日"观念的来源分析
该观念源于将两个不同层面的"5 d"合并理解。
其一,来自诊断标准。"发热≥5 d+≥4项主要临床特征"是经典川崎病的纳入性诊断标准,其目的为保证诊断特异性。该标准回答的是"何时能够确立诊断",而非"何时能够开始治疗"。
其二,来自治疗推荐中的给药时间窗表述。中国2023年指南推荐"最好在发病5~7 d内给予IVIG",AHA 2024年声明的表述为"理想第4~5日(ideally at 4 to 5 days of illness)"。此类表述是对"何时给药冠状动脉结局最优"的经验概括,其方向为约束延迟治疗:越接近该时间窗越好,超过则风险上升。同一声明同时规定,发病10 d以后若炎症持续(CRP>3.0 mg/dL)仍应给予治疗。对超过10 d均不作为绝对界限的时间窗,不构成对发病第4日给药的限制。
此外存在病程日计算的混淆。AHA 2017年声明以括号注明计算方法:发热首日计为第1个发热日。临床常见的两种计算误差:将发热首日记为"第0日",则所谓"第5日"实际为发病第6日;或将前驱症状计入"发病",使时间轴整体前移、治疗相应推迟。
三、指南原文对照
以下截图均取自各指南官方在线版或期刊PDF,红框与紫色高亮为本文所加,原文未作改动。
(一)AHA 2024年科学声明(Circulation 2024;150:e481-e500)
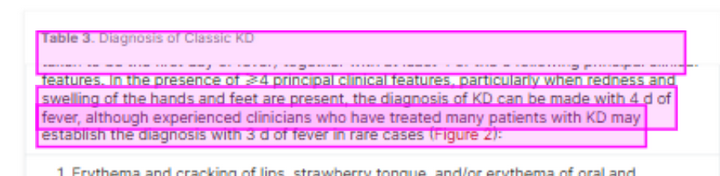
诊断节原文连续两句:
"Diagnosis of KD can be made with 4 days of fever when ≥4 principal clinical criteria are present. Experienced clinicians may establish the diagnosis earlier, at 3 days of fever."
即:≥4项主要临床特征时,发热4 d即可诊断;有经验的医师可提前至发热3 d诊断。注:《World J Pediatr》2025年述评将该句转述为"five days of fever",与AHA 2024年声明正式发表文本"4 days"不一致;查该声明2025年两份勘误均未涉及此句(详见下图图注),应以Circulation在线版为准。

治疗时机表述见于同一文件:
"It is imperative to diagnose KD within 10 days of fever onset, ideally at 4 to 5 days of illness for patients with complete KD, and as soon as possible and within 10 days of fever onset for patients with a possible diagnosis of incomplete KD."
"ideally at 4 to 5 days"的方向为"不应迟于发病第4~5日",而非"不应早于发病第5日";对不完全型川崎病同样要求"尽早、10 d内"。

(二)AHA 2017年科学声明(现行治疗推荐的出处)
治疗推荐第1条(Ⅰ类推荐,证据水平A):
"…should be treated with high-dose IVIG (2 g/kg given as a single intravenous infusion) within 10 days of illness onset but as soon as possible after diagnosis (Class I; Level of Evidence A)."
正文另有同义表述:"所有满足AHA诊断标准的患者,应在病程中诊断能够确立的最早时点接受治疗。"

(三)中国《中国儿童川崎病诊疗循证指南(2023年)》
诊断节(官方PDF第4页):
"有经验的临床医生可能会在仅有发热3 d,因其他典型临床表现均已出现而做出诊断。"

治疗部分推荐意见1(第5页):
"KD确诊后,推荐尽早开始大剂量IVIG治疗。推荐剂量及疗程:单剂量IVIG(2 g/kg)通常在12~24 h内静脉滴注给药。(高质量证据,强推荐)"

关于不完全型川崎病(第5页):"IKD患儿应在诊断明确后立即接受IVIG治疗。"

推荐意见2(第5页)规定了10 d界限的另一端:发病超过10 d的患儿,排除其他原因引起的持续发热,伴ESR或CRP升高,或炎症指标升高合并冠状动脉病变者,仍需给予IVIG治疗。
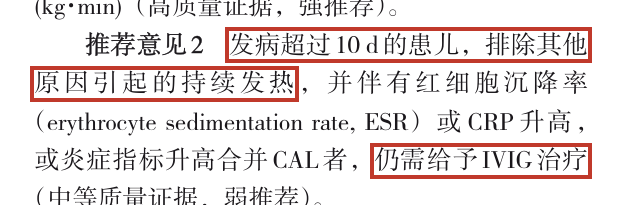
(四)日本第6版诊断指南(2020年)
《World Journal of Pediatrics》2025年述评(浙江大学医学院附属儿童医院团队)对该修订版的转述如下:
"Revision of Diagnostic Guidelines for Kawasaki Disease (6th revised edition) … no longer emphasizes that fever must persist for longer than five days, but rather highlights a comprehensive assessment of clinical presentations. The number of days of fever is not the most important diagnostic criterion."
即:第6版不再强调发热必须超过5 d,转而强调对临床表现的综合评估;发热天数并非最重要的诊断标准。

修订依据可查日本川崎病学会官网发布的《川崎病診断の手引き改訂6版 作成の目的、経緯と変更点》(改订委员会委员长、学会会长署名)原文:
"主要症状の発熱に関して、「5日以上続く」と「(ただし、治療により5日未満で解熱した場合も含む)」を削除し、発熱の日数は問わないことになった。"
即:主要症状中的发热项删除了「5日以上続く」(持续5日以上)与「(ただし、治療により5日未満で解熱した場合も含む)」(但包括经治疗在5日以内退热者)两处限定,对发热天数不再作规定。该文同时说明修订理由:现行治疗中90%以上患者接受单次大剂量输注,约10%于第3病日以前、约35%于第4病日以前即开始IVIG治疗,坚持"不满5日不满足发热项"的判断已与治疗现状不符。皮疹项的表述由"不定形发疹"改为"发疹",并注明"包括BCG(卡介苗)接种痕发红"(原文:従来「不定形発疹」とされていた皮膚症状に、(BCG接種痕の発赤を含む)を記載した)。


(五)加拿大儿科医学会(CPS)实践要点
"10个发热日内输注一剂IVIG(2 g/kg),冠状动脉瘤风险降至5%以下;第10日以后,若发热与炎症持续,仍应治疗。"该文件表1另附脚注:≥4项主要临床标准时,发热第4日即可确诊。

(六)美国风湿病学会/血管炎基金会(ACR/VF)2021指南
该指南采用GRADE体系。其摘要表述为:所有川崎病患者均应接受IVIG初始治疗(良好实践声明);"不完全型川崎病的及时治疗"列为强推荐;整套推荐的核心为"在疾病起病时及时使用已确立的疗法,以最小化患者风险"。
综上,上述六份文件中均无"需等满5个发热日方可输注IVIG"的表述。
四、研究证据
(一)IVIG疗效的确立
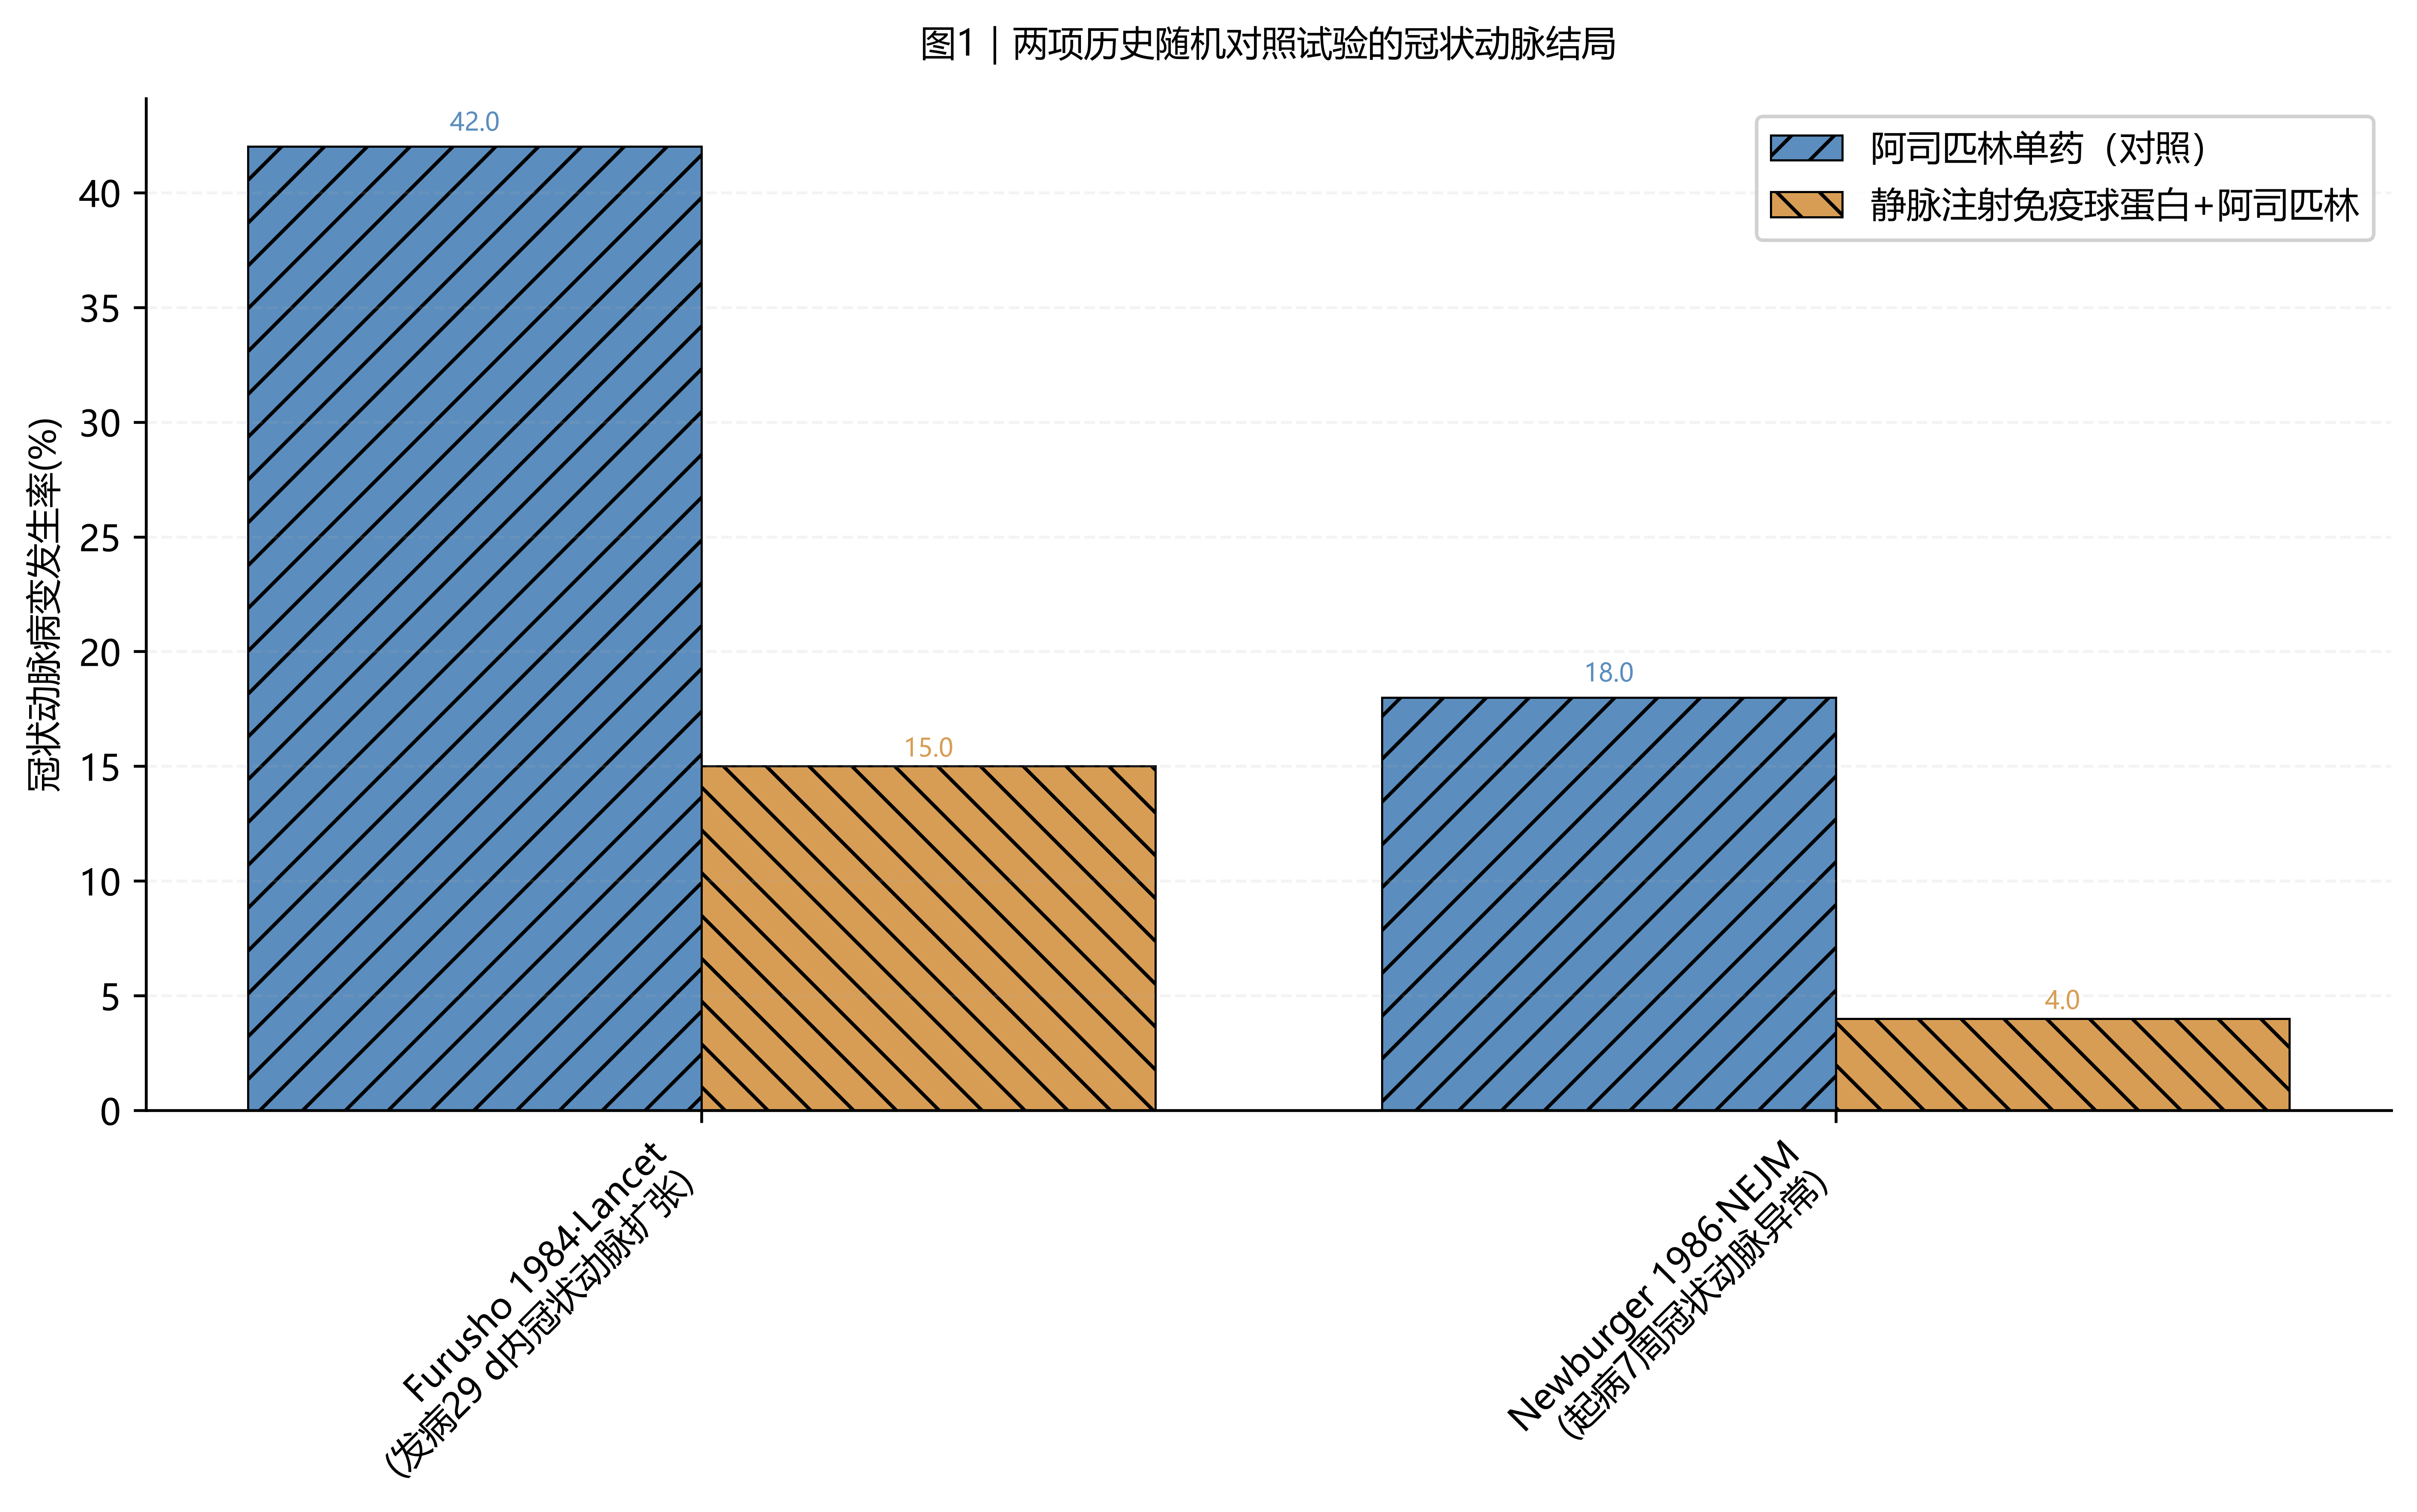
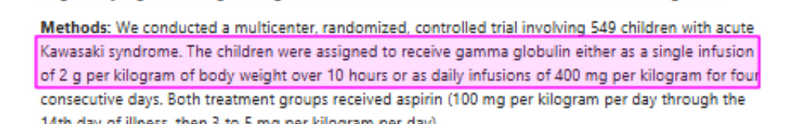
1984年,Furusho等在《柳叶刀》发表首个IVIG多中心对照试验:阿司匹林单药组发病29 d内冠状动脉扩张发生率42%,IVIG联合阿司匹林组15%。1986年,Newburger等在《新英格兰医学杂志》发表美国多中心随机对照试验(RCT):起病7周冠状动脉异常发生率,阿司匹林单药组18%,IVIG组4%。1991年,同一团队完成549例RCT,确立现行方案:2 g/kg单剂、约10 h输注。与400 mg/kg连用4 d相比,单剂组退热更快(住院期间平均体温更低、平均热程更短),炎症指标(CRP、白蛋白、α1-抗胰蛋白酶)恢复更快;冠状动脉异常相对患病率(四剂组对单剂组)2周时为1.94(95%CI 1.01~3.71),7周时为1.84(95%CI 0.89~3.82,后者差异无统计学意义),即冠状动脉结局的组间差异在7周时未达统计学意义。


上述时间窗划定于IVIG疗效获得确证之后,目的是使疗效最大化、防止延迟治疗。
(二)早期治疗的安全性
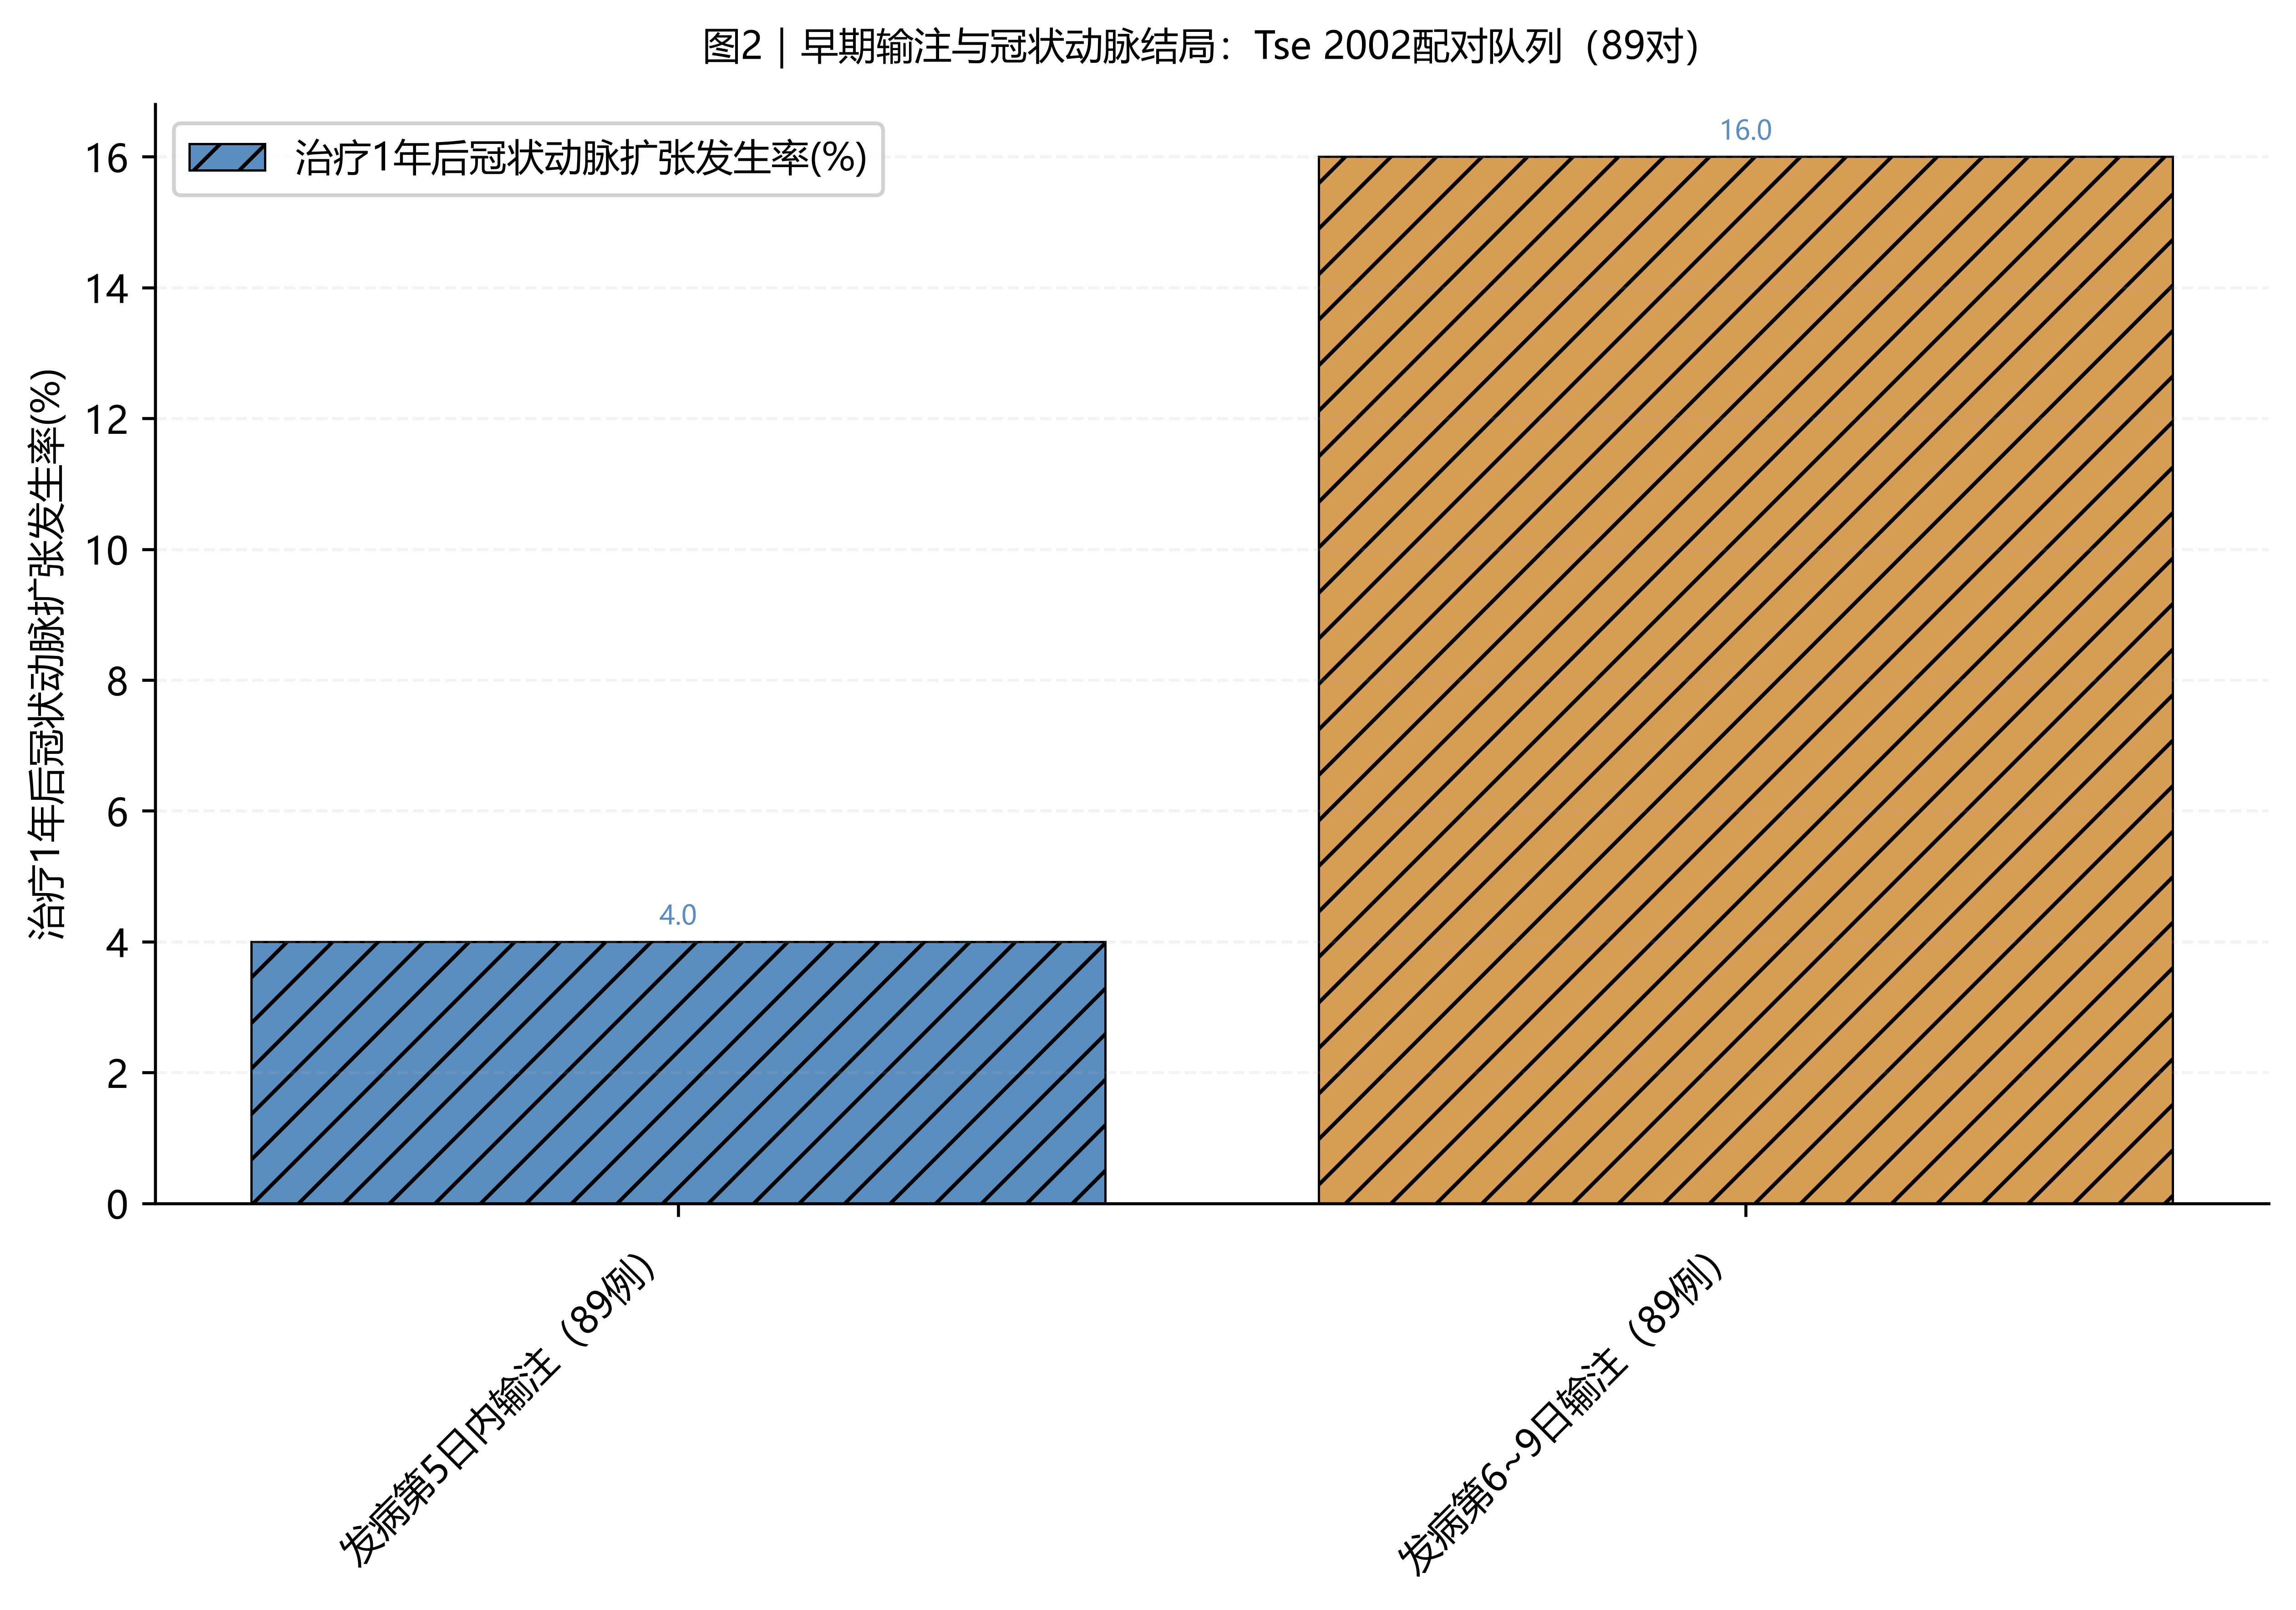
Tse等(多伦多病童医院)2002年发表于《儿科学杂志》的研究采用89对配对设计:一组于发病第5日内给予IVIG,一组于发病第6~9日给予,按诊断时间配对。主要结果:早期组治疗1年后冠状动脉扩张发生率4%,晚期组16%(P=0.02);两组在治疗失败、追加IVIG、加用糖皮质激素、住院时长及3个月内动脉瘤发生率方面差异均无统计学意义。早期组输注后热程较晚期组长约0.7 d。需注意该研究为回顾性配对设计,两组急性期基线并非完全均衡:早期组血清白蛋白更高(36±5 g/L对33±5 g/L,P<0.01)、ALT更高(115±155 U/L对46±49 U/L,P<0.001)、血小板计数更低(354±131×109/L对403±166×109/L,P=0.02),两组疾病特征的差异可能构成混杂,结果解读时应予注意。
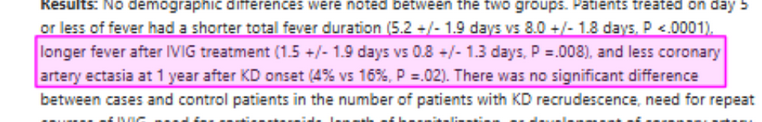
(三)"早期治疗疗效差"说法的分层验证
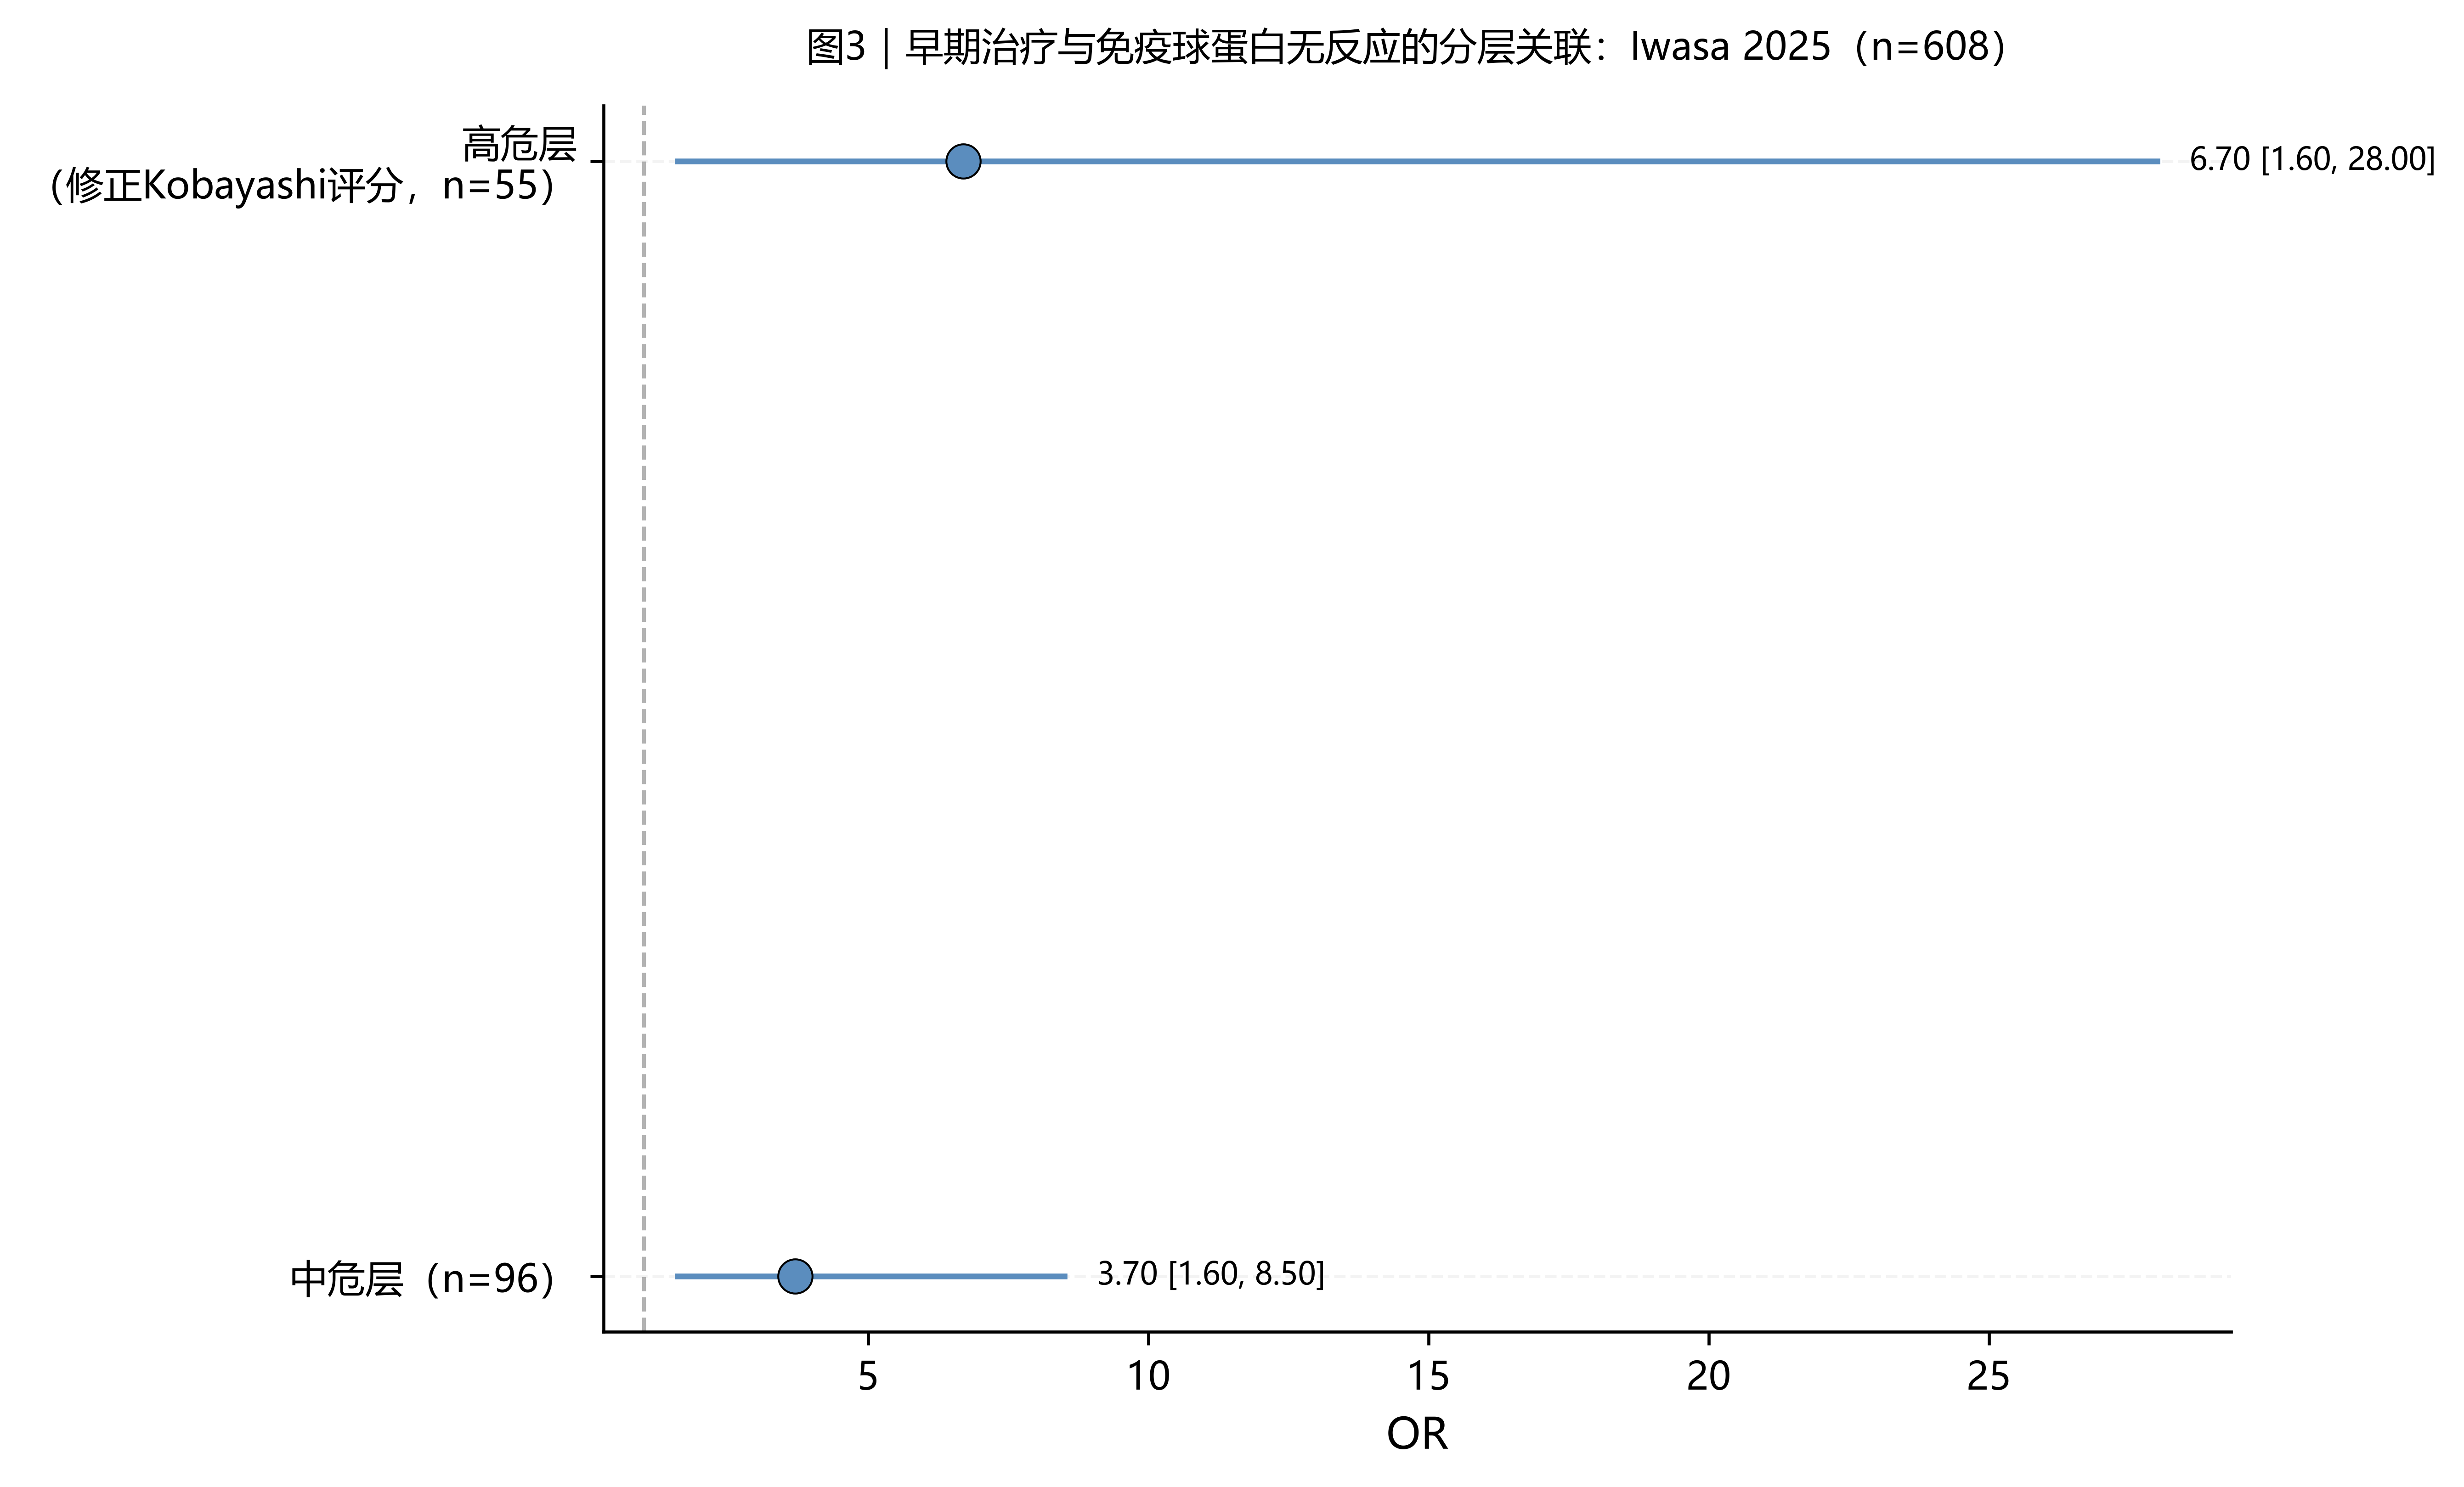
日本研究曾观察到发病第4日前给药者IVIG无反应率偏高。Iwasa等(名古屋,2025年,n=608)按病情严重度分层分析:早期治疗(发病第4日前)IVIG无反应率升高仅见于高危层(OR 6.7,95%CI 1.6~28)与中危层(OR 3.7,95%CI 1.6~8.5);低危与极低危层早期与晚期治疗差异无统计学意义。

AHA 2017年声明对此的概括为:多项研究显示发病第5日前治疗不增加冠状动脉异常;一项日本研究显示发病第1~4日治疗组冠状动脉异常发生率10%、发病第5~7日组5.3%。故不必早于诊断确立盲目给药,但诊断确立后不应延迟治疗。
五、川崎病治疗的时间框架
将上述指南原文归类,川崎病治疗相关的时间规定可分为三层:
| 层级 | 规定 | 依据 |
|---|---|---|
| 时限 | 发病10日内治疗;超过10日若炎症持续仍应治疗 | AHA 2017(Ⅰ类推荐);CPS;中国2023年指南推荐意见2 |
| 时间窗 | 完全型川崎病以发病第4~5日(AHA 2024)或发病第5~7日(中国2023)给药冠状动脉结局最优 | 各指南"最好/ideally"表述,用于约束延迟治疗 |
| 指征 | 确诊即治:≥4项主要特征+相应发热天数(或有经验医师于发病第3日)确立诊断、排除需与川崎病相鉴别的疾病后,给予治疗 | AHA 2017 Ⅰ类推荐/证据水平A;AHA 2024;中国2023年指南"确诊后尽早" |
"需等到发病第5日方可用药"的理解,实际是以日历替代了指征层的"确诊",并将时间窗层的上限作为了下限。
六、回到临床
就本文第一节的病例分析:患儿发病第3日,五项主要临床特征齐备,四项病原学检测阴性,CRP、ESR、ALT同步升高,需与川崎病相鉴别的疾病已基本排除,完全型川崎病诊断可以确立。按照AHA 2024年声明(Class 1)与中国2023年指南("有经验的临床医生可能会在仅有发热3 d……做出诊断"),该患儿具备静脉注射免疫球蛋白的治疗指征;于发病第3~4日给予IVIG 2 g/kg,符合各指南"确诊后尽早、理想为发病第4~5日"的规定。本例超声心动图未见冠状动脉异常(Z值<2),不属高危(高危定义为年龄<6个月或冠状动脉Z值≥2.5),按标准方案(IVIG联合阿司匹林)治疗。
关于IVIG无反应:本例SAA>200 mg/L、ALT升高,属于IVIG无反应风险相对偏高者。AHA 2024年声明对IVIG无反应(IVIG-resistant KD)的界定为首次输注结束后≥36 h仍有持续或再次发热;中国2023年指南推荐意见3的界定为"IVIG初始治疗36 h至2周,仍有任何程度的持续性或者反复性发热"(无反应型KD,即IVIG抵抗型KD),建议尽早再次应用IVIG 2 g/kg,或在IVIG基础上联合糖皮质激素或英夫利昔单抗(中等质量证据,强推荐)。两份文件的判定时窗宽窄不同,应用时应注意版本差异。未经治疗者冠状动脉瘤风险约25%。
需要说明的是,"确诊即治"不等于提早盲目给药:诊断尚未确立、需与川崎病相鉴别的疾病尚未排除时,不必为满足时间窗而提前给药。AHA 2017年声明以"in rare cases"(罕见病例)限定这一表述;其审慎所指为诊断的确定性,而非给药日期。
主要参考文献
- Jone PN, Tremoulet A, Choueiter N, et al. Update on Diagnosis and Management of Kawasaki Disease: A Scientific Statement From the American Heart Association. Circulation. 2024;150(23):e481-e500. 可访问网址:https://www.ahajournals.org/doi/10.1161/CIR.0000000000001295。
- McCrindle BW, Rowley AH, Newburger JW, et al. Diagnosis, Treatment, and Long-Term Management of Kawasaki Disease: A Scientific Statement for Health Professionals From the American Heart Association. Circulation. 2017;135(17):e927-e999. 可访问网址:https://www.ahajournals.org/doi/10.1161/CIR.0000000000000484。
- 中国儿童川崎病诊疗循证指南(2023年). 中国当代儿科杂志. 2023;25(12):1198-1210. 可访问网址:https://www.zgddek.com/CN/10.7499/j.issn.1008-8830.2309038。
- Kobayashi T, Ayusawa M, Suzuki H, et al. Revision of diagnostic guidelines for Kawasaki disease (6th revised edition). Pediatr Int. 2020;62(10):1135-1138. 可访问网址:https://pubmed.ncbi.nlm.nih.gov/33001522/。修订说明(目的、经过与变更点)见日本川崎病学会官网:https://jskd.jp/川崎病関連情報/診断の手引き/。
- Tong S, Gong F. Navigating the 2024 AHA guidelines for Kawasaki disease: practical insights for clinicians. World J Pediatr. 2025;21(4):369-371. 可访问网址:https://doi.org/10.1007/s12519-025-00892-9。
- Canadian Paediatric Society. Kawasaki disease: Practical guidance on diagnosis and management. Paediatr Child Health. 2025;31(5):550-555. 可访问网址:https://cps.ca/en/documents/position/kawasaki-disease。
- Gorelik M, Chung SA, Ardalan K, et al. 2021 American College of Rheumatology/Vasculitis Foundation Guideline for the Management of Kawasaki Disease. Arthritis Rheumatol. 2022;74(4):586-596. 可访问网址:https://pubmed.ncbi.nlm.nih.gov/35257501/。
- Furusho K, Kamiya T, Nakano H, et al. High-dose intravenous gammaglobulin for Kawasaki disease. Lancet. 1984;2(8411):1055-1058. 可访问网址:https://pubmed.ncbi.nlm.nih.gov/6209513/。
- Newburger JW, Takahashi M, Burns JC, et al. The treatment of Kawasaki syndrome with intravenous gamma globulin. N Engl J Med. 1986;315(6):341-347. 可访问网址:https://pubmed.ncbi.nlm.nih.gov/2426590/。
- Newburger JW, Takahashi M, Beiser AS, et al. A single intravenous infusion of gamma globulin as compared with four infusions in the treatment of acute Kawasaki syndrome. N Engl J Med. 1991;324(23):1633-1639. 可访问网址:https://pubmed.ncbi.nlm.nih.gov/1709446/。
- Tse SM, Silverman ED, McCrindle BW, Yeung RS. Early treatment with intravenous immunoglobulin in patients with Kawasaki disease. J Pediatr. 2002;140(4):450-455. 可访问网址:https://pubmed.ncbi.nlm.nih.gov/12006960/。
- Iwasa M, Aoki G, Inukai S. Association between the timing of intravenous immunoglobulin treatment and severity of Kawasaki disease. Mod Rheumatol. 2025;35(4):707-714. 可访问网址:https://pubmed.ncbi.nlm.nih.gov/39820494/。
截图与图表说明:AHA 2017/2024截图取自Circulation在线版;中国2023年指南截图取自《中国当代儿科杂志》官方PDF(第4、5页);CPS截图取自加拿大儿科医学会官网(cps.ca);WJP 2025截图取自Springer在线版;日本第6版修订说明截图取自日本川崎病学会官网;历史研究截图取自PubMed官方摘要页。红框与紫色高亮均为本文所加,原文未经改动。每张截图的高亮位置均依据页面文本的精确坐标定位并经逐张核验。三张数据图按原始文献数据绘制。
声明:本文供专业交流,不构成对具体患者的诊疗建议;临床决策请结合患者实际情况并遵循所在医疗机构的规范。引用AHA 2024年声明时请注意其2025年两份勘误(2025-02-24、2025-03-31),内容为表2/表3与图1格式的修订,不涉及本文所引诊断与治疗时机语句。